


The functional orthodontic appliance continues to be the ideal solution in the treatment of the dental alveolar-skeletal wrong bite at the prepubertal skeletal development age (girls 9-12 years old; boys 10-14). The advantage, still irreplaceable by any other method of treatment, is that it reducesthe discrepancies of the position of the jawsin relation to each other and to the base of the skull, in the shortest treatment time and with maximum efficiency.
After the eruption of the permanent teeth and the possible application of the fixed appliance and of the intermaxillary elastic tractions, reducing the skeletal wrong bite is usually not treatable anymore because the maximum somatic skeletal curve development has long been exceeded. From this point, the reduction of the wrong bite can only be treated by traumatizing surgical-orthodontic methods with many risks, or with fixed appliance and intermaxillary traction where the frequency of relapse exceeds 80% of the treated cases.
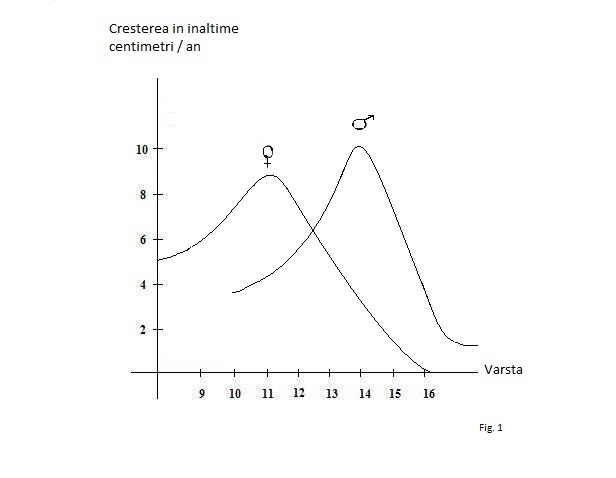
Why is SANDER II so efficient?
Most of the action of the functional orthodontic appliance is applied to the dental alveolar and jaw tissue and to the temporo mandibular joint.
During sleep.
From the first phase of the installation of the shallow sleep, REM I, and in all the other phases, the muscles go into the relaxation phase, at the level if the jaws takes place a disocclusion between 0.7 to 1.0 cm.
 Thus, the contact with the conventional orthodontic appliance sych as activator or bionator types is lost and implicitly its therapeutic action.
In contrast, the SANDER II appliance, through the guiding pins, which remain in contact with the mandibular guiding plane of the appliance even at the disoclussion of over 12 mm, it continues its therapeutic action throughout the sleep using the visco-elasticity of the periarticular temporo mandibular tissues.
Therefore, the treatment time, even with the large deviations from the normal cephalometric values, is reduced to one quarter of the time that would be necessary for another functional appliance (bionator or activator type).
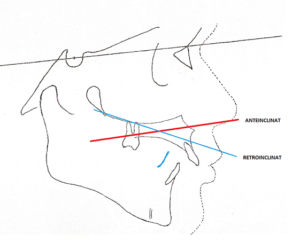 By positioning the guiding pins in an inclination between 55-65 °, together with the protrusion of the mandible, can be corrected pre- or retro-inclination of the jaw.
The patients who wear SANDER II appliance are comfortable talking with the appliance in the mouth resulting in increased acceptance. By wearing it during the day it exerts a drive that stimulates the patient to position the mandible sagittally in the neutral occlusal position already programmed by he occlusion reconstructed by the SANDER II appliance.
The SANDER II appliance is composed of two parts (maxillary and mandibulary), makes it possible, additionally, also to correct the individual positions of the teeth through active elements (elastic springs, screws).
In the cases of restricted, poor nasal breathing, or oral breathing, it is not recommended to use the activator or bionator treatment, here it’s of a major indication and superior efficiency to use the Sander II protrusion appliance.
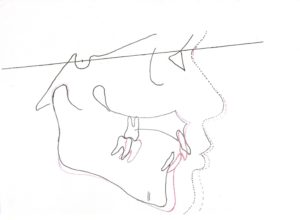
We exemplify here the case of a patient who presented with a proeminent retruded position of the mandible, skeletally Class Angle II, with distalized occlusion and sagittal frontal non-occlusion of 9mm.
The ANB angle is by +3° higher than normal, which can be reduced through a functional Activator Bionator appliance in about 6 years of disciplined and uninterrupted treatment. Because, as described in the specialty literature and confirmed in the clinical practice, the activator or the bionator achieves a maximum reduction of only 0.5 °/year!.
Indubitable performance, also much confirmed clinically, the efficiency in the treatment of this anomaly with the SANDER II appliance, is that it can reduce the ANB angle by 2°/year !. Which would allow the decrease in the the ANB angle, in the case shown above, in only 1.5 years of treatment!
The complementary treatment, which eventually should continue with fixed orthodontic appliances would be necessary only for a short time, and the corrections it will have to produce will be much easier in terms of difficulty.
Such a succession of the appliance involved has been scientifically certified, it prevents through a highly superior proportion the occurrence of relapses, as it was shown above.
Conclusions:
Working currently and reccomending in the treatment of Angle abnormalities class II the protrusion appliance SANDER II, can conclude after long practice in the Sirona Clinic, th functional appliance was established as a treatment instrument with excellent results in short time without the risk of relapse.
We order the appliances to be manufactured exclusively at the ADVANCED GERMAN ORTHODONTICS laboratory, specialized in functional orthodontic appliances.
The results obtained and the patient acceptability and the increased comfort offered to the patients with this method of treatment, justifies its choice with predilection in the right moment for somatic development.


